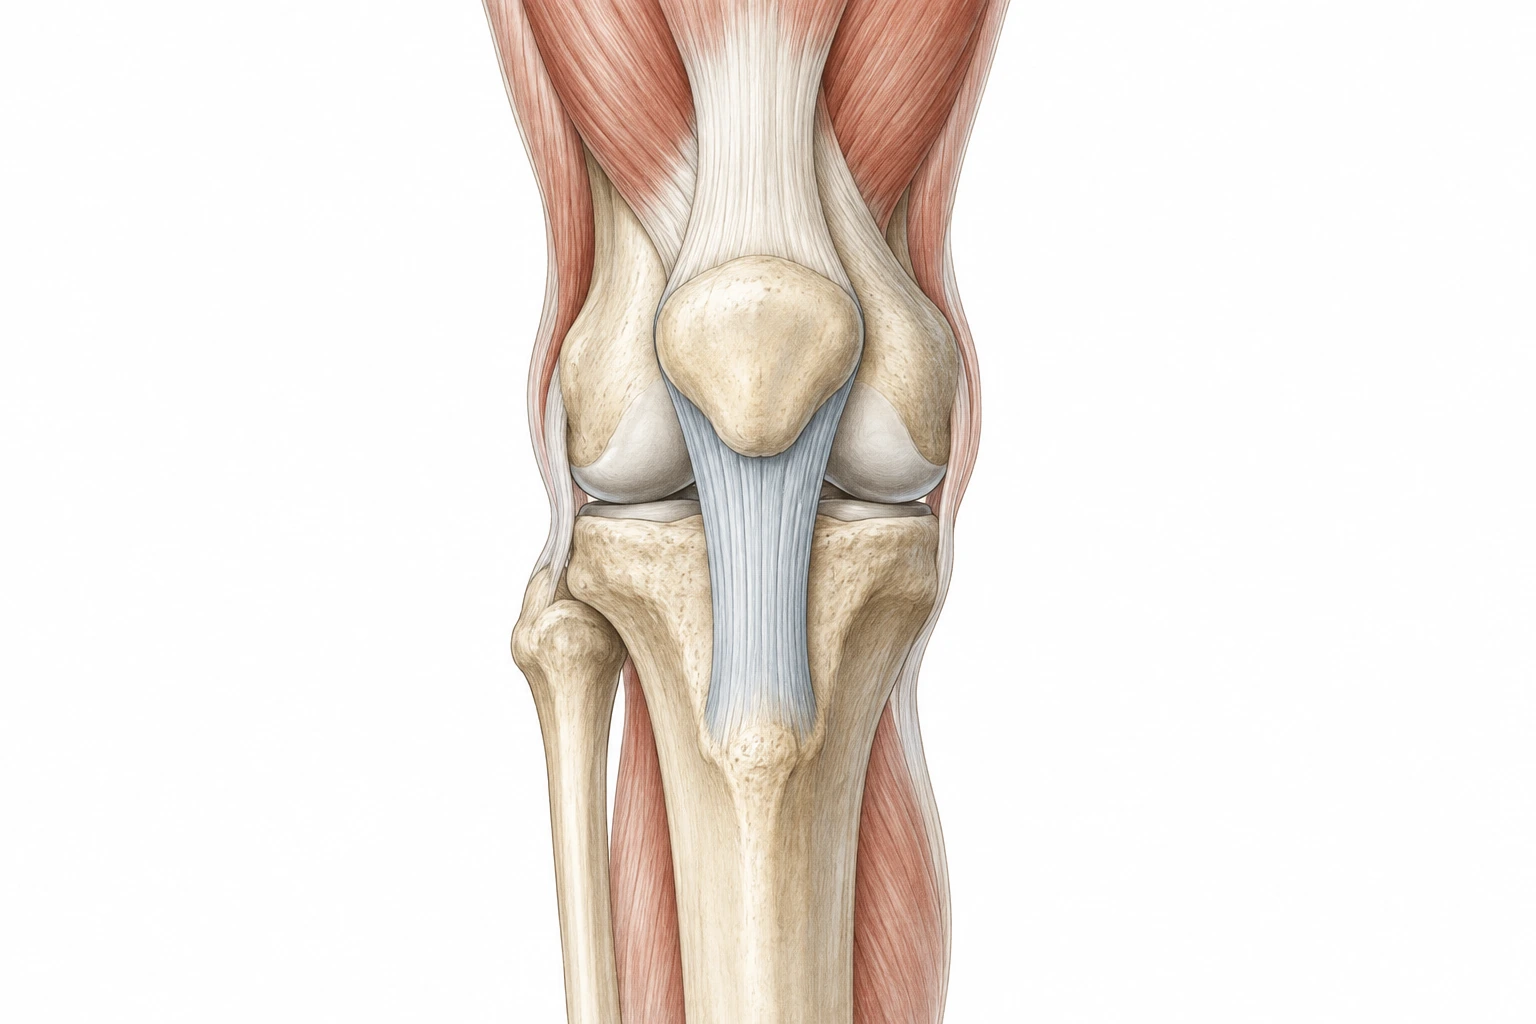
What do we know about the added value?
The relevant question is not only whether people feel better after shockwave. Knee symptoms can also change due to exercises, custom sports load, time and expectations. In order to assess the contribution of shockwave, research is needed in which a comparable group is given the same basic care with a control treatment.
The guideline on additional treatments for patellate dinopathy Evaluate the evidence with restraint. Shockwave appears to be able to give little or no difference in pain in placebo comparisons; the certainty of the evidence is low. That does not justify a promise that a persistent jumper's knee will be solved with a few sessions.
A story of someone who responded well can be valuable as a personal experience. It doesn't tell you how big your chances of benefit are or which part of the overall trajectory helped. Therefore, ask for comparative studies for the patellar tendon, not for success stories about another tendon or another part of the body.
Why do you read different advices?
Thuisarts advises with a jumper knee not to use shockwave, because research doesn't show that it helps. After at least 12 weeks without improvement, the specialized guideline offers scope to consider additional treatment, along with exercises and explanations on the lack of proven effect.
Those wordings are not identical. One source opts for clear patient advice against use; the other describes a possible individual consideration in case of insufficient result. Neither supports shockwave as a natural first treatment or as a guaranteed solution after exercise is disappointing.
Ask a clinician who proposes shockwave to discuss this difference. A careful explanation also includes the possibility to abandon it. The fact that a technique is available is not in itself a medical reason to add it.
See first what has actually been tried
Having 12 weeks of symptoms is not the same as 12 weeks of appropriately supervised practice. A patient may have been in pain for months, but only occasionally did stretching. Another has built up carefully, while the total sports load remained high. These are different starting points.
Make an overview of the basic treatment in advance:
- What diagnosis was made and what was it based on?
- What strength and load structure did you follow?
- How did the program fit between training, competitions and work?
- Which exercises were executable and which one did you have to skip?
- What turned into stairwells, training and the reaction the next day?
The guideline on practice therapy describes a gradual route from education and strength to sports-specific loads. The absence of a fully appropriate structure can be a reason to first improve the existing plan without adding a new treatment.
A trial treatment requires clear appointments in advance
When a trial of shockwave is considered after consultation, it should be clear what you want to achieve with it. Less pain during one exercise is another goal than to tolerate a full volleyball training. Choose a viable activity that you can assess in a similar way before and after the test.
One example: your goal is to perform an agreed part of the training without any obvious deterioration the next morning. Before the test, note how much participation is successful and how the knee reacts to it. Also agree on what time you're evaluating. Without initial status, it becomes difficult to distinguish small fluctuations from significant progress.
Capture which other parts remain the same and which changes. In practice, not everything needs to stand still, but a simultaneous modification of five treatments makes the explanation of result uncertain. That uncertainty is part of the evaluation, especially if you decide to repeat a route later.
Focused, radial and the temptation of a stronger device
There are several shockwave techniques and treatment protocols. This difference does not automatically mean that a more intensive setting or a more expensive device gives better results at the patellar tendon. A general technical explanation is not evidence of clinical added value for your symptom.
Ask which research is in line with the technique used, your diagnosis and the chosen combination with exercises. Also EMTT should not be presented as proven reinforcement for the patellar tendon on the basis of a specific shoulder symptom. This requires own, indicative justification.
Also discuss treatment load, possible after pain and costs. Time and money are real parts of a choice when advantage is uncertain. You don't have to try every available additional technique before serious treatment is involved.
When is stopping or re-evaluating more logical?
The specialized guideline recommends that a test should be carried out in good time and that it should be stopped at little or no effect. Extending a route without measurable progress is not appropriate for a critical assessment. A new promise about a few more sessions is not a substitute for research into why the plan is not working properly.
In the absence of recovery, diagnosis, load and treatment should be reviewed. That doesn't mean the pain is imagined or you're showing insufficient commitment. It means that the current statement and approach must be re-examined. Sometimes adaptation of basic care is more useful than a subsequent supplementary treatment.
Frequently asked questions
Is shockwave proven effective for a jumper's knee?
Convincing evidence of added value is missing. The specialist guideline assesses the available results as uncertain and Thuisarts does not recommend shockwave. A treatment proposal should explain these limitations, even when the provider mentions positive practical experiences.
Then why does a clinic offer it anyway?
A trader can discuss an individual additional test in the event of persistent symptoms. That's something other than proven added value. Ask for the purpose, the justification for your diagnosis, the alternatives, the costs and the pre-arranged reason to quit.
Do I need to pause my exercises during shockwave?
The specialist guideline discusses a possible addition to practice therapy. Whether a particular load is temporarily adjusted depends on the response and treatment plan. Make those appointments concrete; do not stop or increase your program just because a session is scheduled.
How many sessions are needed?
There is no number that guarantees success. The guideline describes evaluation after a limited trial and stops at little or no effect. An offer of a fixed package should not replace that assessment. Let the sequel depend on your functioning and the agreed goals.
Sources and evidence
- Anterior knee pain guideline: additional conservative treatments in PT (2022) ↗
Uncertain added value of shockwave; any addition only after sufficient basic treatment and with evaluation.
- Thuisarts: I have a jumper knee ↗
symptom pattern, recovery, when to contact and reluctant advice on shockwave.
- Anterior knee pain guideline: practice therapy in patella tendinopathy (2022) ↗
Education and progressive practice therapy as a basis; staged construction towards sports-specific stress.
A personal follow-up step
From insight
to an appropriate plan.
At a paid intake, we'll discuss your symptom and do targeted research. ultrasound is included at no extra cost when it makes sense. Any treatments are agreed separately.
View the initial consultation